In brief
- Integrated clinical, genomic and transcriptomic profiling was performed on 400 patients with resected stage IA to IIIA EGFR-mutant lung adenocarcinoma.
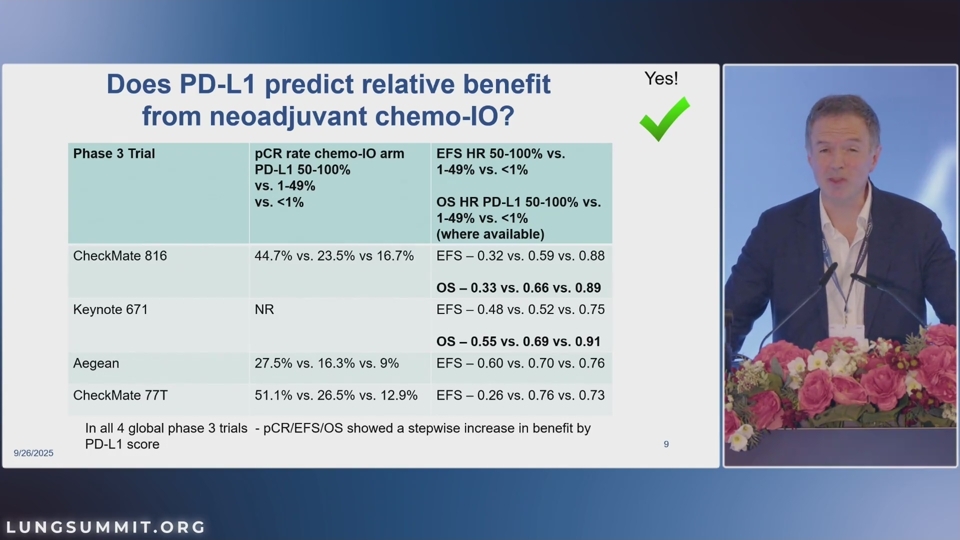
- The multi-omic model reached a median concordance index of 75.4% across one internal and three external validation cohorts.
- Transcriptomic features predicted recurrence risk more accurately than clinical or genomic variables used alone.
- TP53 co-mutations, copy number alterations and APOBEC-associated mutational signatures increased with pathological stage. RBM10 co-mutations were enriched in tumours carrying L858R mutations and correlated with upregulation of WNT signalling and epithelial-mesenchymal transition.
- The model separated recurrence risk within individual stages, including stage I. No hazard ratio, per-cohort index or follow-up duration is reported, and the authors state that prospective validation in larger cohorts will be required.
Study at a glance
- Cohort: 400 patients with resected EGFR-mutant lung adenocarcinoma
- Population: Pathological stage IA to IIIA
- Profiling: Integrated clinical, genomic and transcriptomic data
- Validation: One internal and three external cohorts
- Performance: Median concordance index of 75.4%
- Stated application: Identifying patients most likely to benefit from adjuvant EGFR TKI
- Not reported: Per-cohort indices, hazard ratios, follow-up duration, recurrence numbers, prospective validation
A median concordance index of 75.4% across four validation cohorts
The model was built from clinical, genomic and transcriptomic data together and tested in one internal and three external cohorts, and the authors describe its performance as superior and reproducible. A concordance index measures how often two patients are ranked in the correct order for recurrence, so 75.4% describes discrimination and not an absolute risk for any patient. The abstract gives the median alone: no value for any single cohort, no confidence interval, and no figure for the stage-based approach the model is offered against.
TP53, copy number alterations and APOBEC signatures rose with stage, and RBM10 clustered with L858R
Genomic instability tracked with stage. TP53 co-mutations, copy number alterations and APOBEC-associated mutational signatures all increased with pathological stage, so they carry information that stage already carries. RBM10 co-mutations were enriched in tumours with L858R mutations and correlated with upregulation of WNT signalling and epithelial-mesenchymal transition, a correlation within this cohort with no recurrence figure attached to it. Transcriptomic features predicted recurrence more accurately than the clinical or genomic variables alone, although no figure is reported for those single-modality models.
Stratification inside stage I, against an adjuvant standard set by pathology alone
Adjuvant osimertinib is the standard of care for resected stage IB to IIIA EGFR-mutant disease following ADAURA, and adjuvant decisions are guided by pathological stage alone. The authors note that real-world data show up to 40% of patients remain disease-free at five years without it. The model stratified risk within individual stages, including stage I, and the authors state that it identified the patients most likely to benefit from adjuvant EGFR TKI. No trial is reported in which treatment was assigned on the basis of the model, so that benefit is a prediction about who is at risk rather than a measured effect of giving or withholding the drug.
“These findings define the molecular heterogeneity of early-stage EGFR-mutant LUAD and support multi-omic risk stratification to inform adjuvant EGFR TKI decisions beyond pathological stage.”Saw et al., Journal of Thoracic Oncology (2026)
The authors state that prospective validation in larger cohorts will be required to confirm the findings.
Sources
- Journal of Thoracic Oncology. Integrated multi-omic profiling enables recurrence risk stratification beyond pathological stage in resected EGFR-mutant lung adenocarcinoma (2026-09-01). doi.org
Featuring Lung Summit faculty
This study was co-authored by Lung Summit faculty Stephanie Saw.
This article was produced independently by the Lung Summit editorial team, without industry funding or input.