SELECT FROM MENU

Therapy Areas
Drug Classes

       Therapy Areas

All Sessions

All Sessions

Resectable NSCLC

Resectable NSCLC

Advanced NSCLC

Advanced NSCLC

SCLC

SCLC

Biomarkers

Biomarkers

       Drug Classes

Targeted Therapies

Targeted Therapies

Immunotherapies

Immunotherapies

ADCs

ADCs

Advanced NSCLCSeptember 14, 2026

ARROS-1: first-line zidesamtinib responds in over 90% of ROS1-positive NSCLC

Presented by Dr. Alexander Drilon at the IASLC 2026 World Conference on Lung Cancer (WCLC) in Seoul, efficacy and safety data for zidesamtinib in patients with advanced ROS1-positive NSCLC who had never received a tyrosine kinase inhibitor (TKI) show a response rate above 90%, responses that mostly outlast a year, and a complete intracranial response in seven of ten evaluable patients with brain metastases. The results come from the TKI-naive cohort of ARROS-1, the global phase 1/2 trial whose TKI-pretreated results have been reported before.
Share
ARROS-1: first-line zidesamtinib responds in over 90% of ROS1-positive NSCLC

In brief

  • In the TKI-naive cohort of the phase 1/2 ARROS-1 trial, zidesamtinib 100 mg once daily produced an objective response by blinded central review in 88 of 94 patients (94%), or 87 of 94 (93%) counting confirmed responses only.
  • Responses were durable: 94% were still ongoing at 9 months and 86% at 12 months. Median duration of response and median progression-free survival were not reached; 90% of patients were progression-free at 12 months.
  • All 10 patients with measurable brain metastases responded intracranially, 7 of them with a complete intracranial response, and no CNS progression was seen in the 78 patients without brain metastases at baseline.
  • Across 532 patients treated at 100 mg, treatment-related adverse events led to dose reduction in 11% and to discontinuation in 1%; peripheral edema (34%, any grade) was the most frequent treatment-related event.

Study at a glance

  • Trial: ARROS-1 (NCT05118789), sponsored by Nuvalent
  • Design: global, single-arm, first-in-human phase 1/2 trial of zidesamtinib in advanced ROS1-positive NSCLC and other solid tumours; phase 1 dose escalation (25–150 mg once daily) in TKI-pretreated patients, phase 2 cohorts at the recommended dose of 100 mg once daily; sites in the Asia-Pacific region, Europe and North America
  • Population reported here: TKI-naive patients with locally advanced or metastatic ROS1-positive NSCLC, up to one prior line of chemotherapy with or without immunotherapy; 183 TKI-naive patients treated, 94 in the efficacy population (measurable disease by BICR, first dose by 15 June 2025); safety population 532 patients at 100 mg across all lines
  • Arms: none; single-arm, all patients received zidesamtinib 100 mg once daily
  • Primary endpoint of phase 2: objective response rate by blinded independent central review (BICR), RECIST 1.1. Secondary: duration of response, time to response, PFS, OS, intracranial activity, safety, pharmacokinetics, patient-reported outcomes. No formal statistical test was reported
  • Data cut-off 16 April 2026; median follow-up 15.2 months (range 1.1–30.5) in the efficacy population

Four design goals: ROS1 potency, resistance-mutation coverage, brain penetration and sparing TRK

Zidesamtinib is a ROS1 TKI designed to spare TRK. It is approved by the FDA for adults with locally advanced or metastatic ROS1-positive NSCLC who have already received a ROS1 kinase inhibitor, and it remains investigational in the first-line, TKI-naive setting. In his background slides, Dr. Drilon listed the limitations of the FDA-approved frontline ROS1 TKIs that the drug was designed to address: suboptimal activity in the central nervous system, and frequent, dose-limiting CNS adverse events with agents that inhibit TRK as well as ROS1. The four stated design goals for zidesamtinib were activity against ROS1, activity against ROS1 resistance mutations, brain penetrance and minimal TRK inhibition.

Earlier reports from ARROS-1 covered TKI-pretreated patients, including those with ROS1 resistance mutations, CNS disease, and prior repotrectinib or taletrectinib. The Seoul presentation reports the trial’s registrational-intent TKI-naive cohort.

Who was treated: 94 efficacy-evaluable patients out of 629 enrolled

ARROS-1 enrolled 629 patients with any ROS1-positive solid tumour at any dose across its phase 1 and phase 2 parts. Of these, 532 patients with advanced ROS1-positive NSCLC received the phase 2 dose of 100 mg once daily in any line of therapy and form the safety population. The abstract describes this group as 35% from the Asia-Pacific region, 33% from Europe and 32% from North America. Within it, 183 patients were TKI-naive. The efficacy analysis was restricted to the 94 TKI-naive patients with measurable disease by BICR who had started treatment by 15 June 2025, which gave at least nine months of follow-up for duration of response.

In this efficacy population the median age was 59 years (range 26–87), 59% were women and 59% had never smoked. By region, 40% were treated in North America, 31% in the Asia-Pacific region and 29% in Europe. ECOG performance status was 0 in 60% and 1 in 40%; 93% had stage IV disease at study entry. Baseline CNS metastases by BICR, measurable or non-measurable, were present in 16 patients (17%). Prior platinum-based chemotherapy, with or without immunotherapy, had been given to 25 patients (27%); 16 of the 25 had also received immunotherapy, which is the 17% prior-immunotherapy figure in the abstract.

Responses in 93–94% of patients, most lasting beyond a year

The objective response rate by BICR was reported as 94% (88 of 94; 95% CI 87–98) in the presentation and as 93% (87 of 94) in the abstract. The one-patient difference is explained by the presentation’s footnote: its count includes a single-timepoint partial response that was pending confirmation in a patient still on treatment. The confirmed response rate is therefore 93%. Complete responses were recorded in 14 patients (15%), one of them a single-timepoint complete response pending confirmation in a patient with a prior confirmed partial response.

Among the 87 responders, Kaplan-Meier estimates put 96% still in response at 6 months, 94% (95% CI 86–97) at 9 months and 86% (95% CI 75–92) at 12 months. Median duration of response was not reached (95% CI 20 months to not estimable). Progression-free survival in the full efficacy population of 94 was 95% (95% CI 87–98) at both 6 and 9 months and 90% (95% CI 81–95) at 12 months; the median was not reached. No overall survival data were presented.
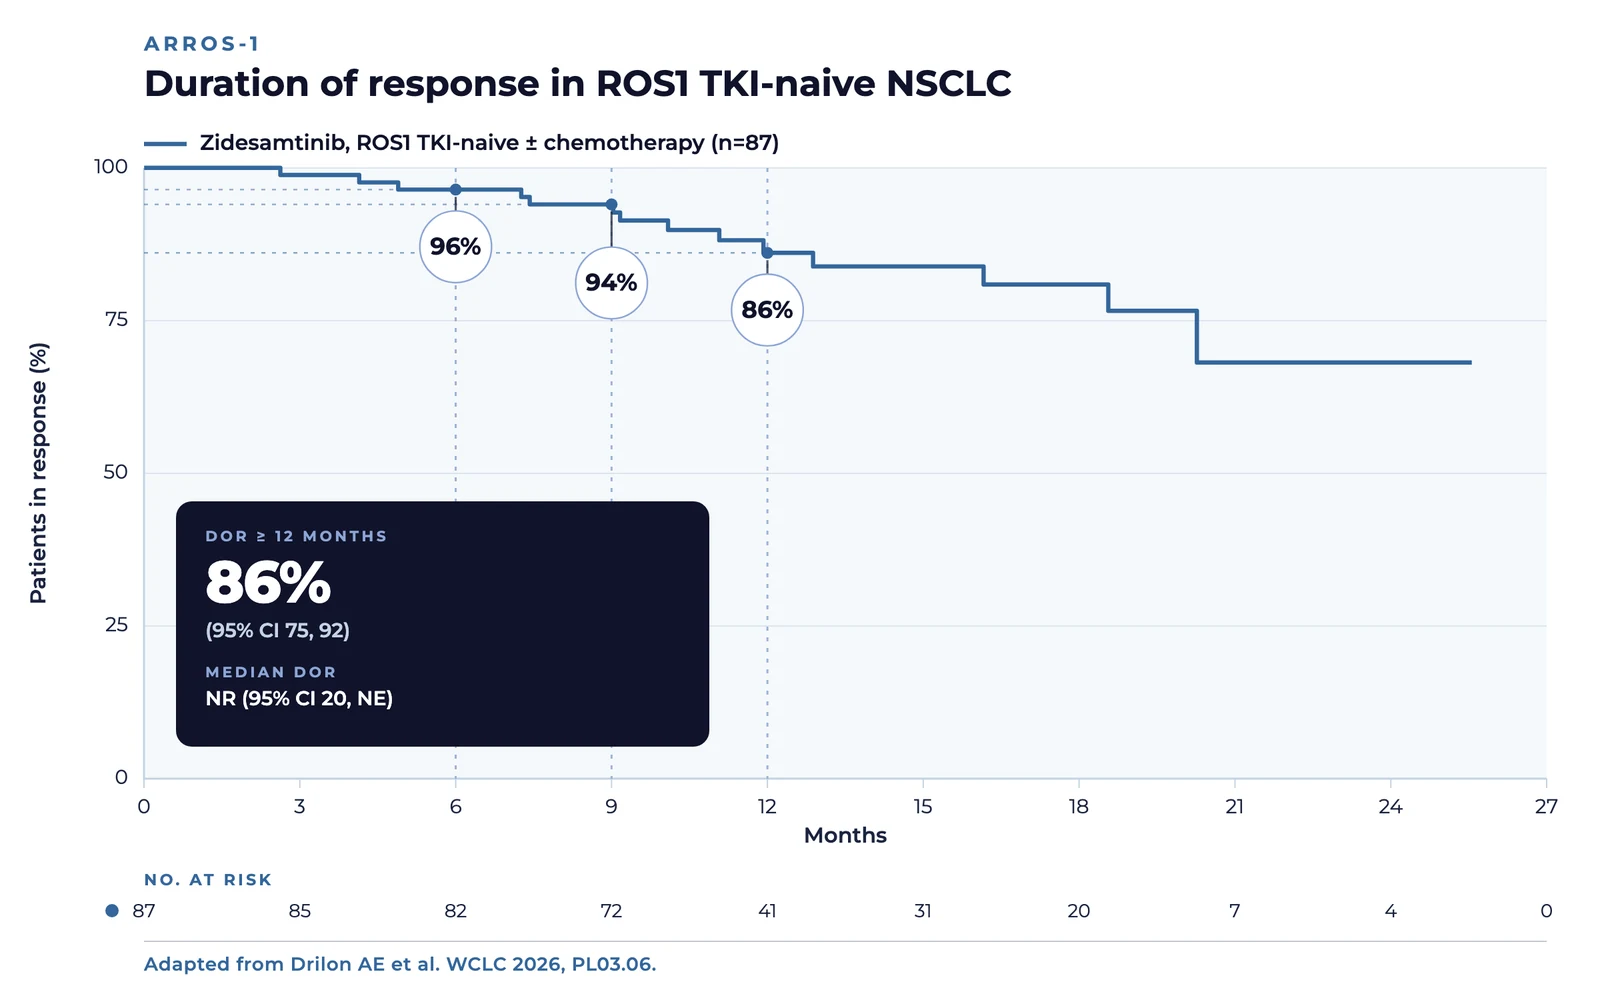
Kaplan-Meier curve of duration of response among the 87 systemic responders to zidesamtinib in the TKI-naive cohort of ARROS-1: 96 percent still in response at 6 months, 94 percent at 9 months and 86 percent at 12 months, with median duration of response not reached. The curve covers systemic responses only.
Figure 1. Kaplan-Meier curve of duration of response in the TKI-naive cohort of ARROS-1, for the 87 patients with a systemic response to zidesamtinib 100 mg once daily (data cut-off 16 April 2026). This curve shows the systemic responders only (n = 87); it does not include the intracranial responses, which are shown separately in Figure 2. Responses were still ongoing in 96% of patients at 6 months, 94% (95% CI 86–97) at 9 months and 86% (95% CI 75–92) at 12 months. Median duration of response was not reached (95% CI 20 months to not estimable) at a median follow-up of 15.2 months. Curve redrawn from the presented figure. Adapted from Drilon A, WCLC 2026, abstract 4707 (PL03.06).
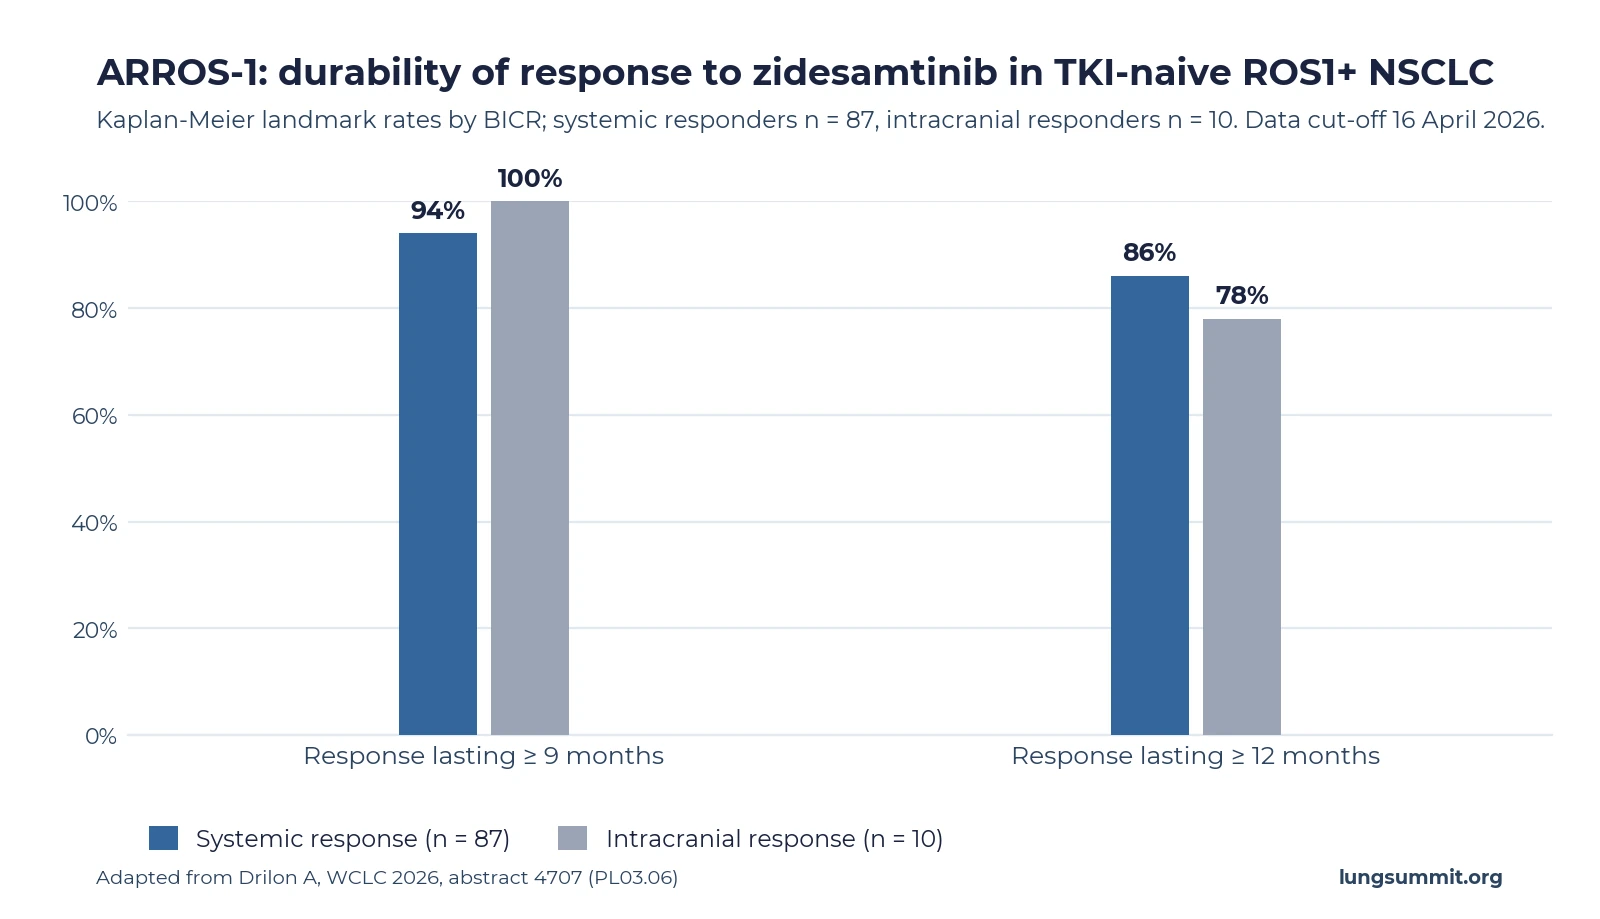
Bar chart of duration-of-response landmarks in ARROS-1: 94 percent of systemic responses and 100 percent of intracranial responses lasted at least 9 months; 86 percent and 78 percent lasted at least 12 months.
Figure 2. Kaplan-Meier estimates of the percentage of responders still in response at 9 and 12 months in the TKI-naive cohort of ARROS-1 (data cut-off 16 April 2026): 94% and 86% for systemic responses (n = 87), and 100% and 78% for intracranial responses in the CNS response-evaluable group (n = 10). Median duration of response was not reached in either group. Adapted from Drilon A, WCLC 2026, abstract 4707 (PL03.06).

Complete intracranial responses in seven of ten patients with measurable brain metastases

Intracranial activity was assessed in a CNS response-evaluable population of 10 TKI-naive patients, defined as those with measurable CNS lesions of at least 5 mm at baseline by BICR and no brain radiation within two months of the first dose. All 10 responded intracranially (intracranial ORR 100%, 95% CI 69–100), and 7 of the 10 (70%) had a complete intracranial response. By Kaplan-Meier estimate, every intracranial response was still ongoing at 6 and 9 months, and 78% (95% CI 36–94) were ongoing at 12 months; the median intracranial duration of response was not reached (95% CI 9 months to not estimable). The wide confidence intervals reflect the size of this group.

A separate observation concerned patients who entered the study without brain metastases. Among the 78 TKI-naive patients with no CNS disease at baseline by BICR, no CNS progression events were observed at the data cut-off.

Peripheral edema leads the adverse-event list; 1% stopped for a treatment-related event

Safety was reported for all 532 patients with advanced ROS1-positive NSCLC who received zidesamtinib 100 mg once daily, whether TKI-naive or pretreated. Treatment-related adverse events occurring in at least 15% of patients were peripheral edema (34% any grade; 0.6% grade 3 or higher), weight increased (18%; 4%), blood creatine phosphokinase increased (18%; 3%), dysgeusia (17%; 0%) and aspartate aminotransferase increased (15%; 1%). Treatment-emergent adverse events of any cause in at least 15% of patients additionally included constipation (23%), alanine aminotransferase increased (18%), dyspnea (17%; 4% grade 3 or higher), arthralgia (17%), peripheral sensory neuropathy (17%), hypertriglyceridemia (16%) and headache (15%). Peripheral edema of any cause was seen in 42% of patients, with 1% at grade 3 or higher.
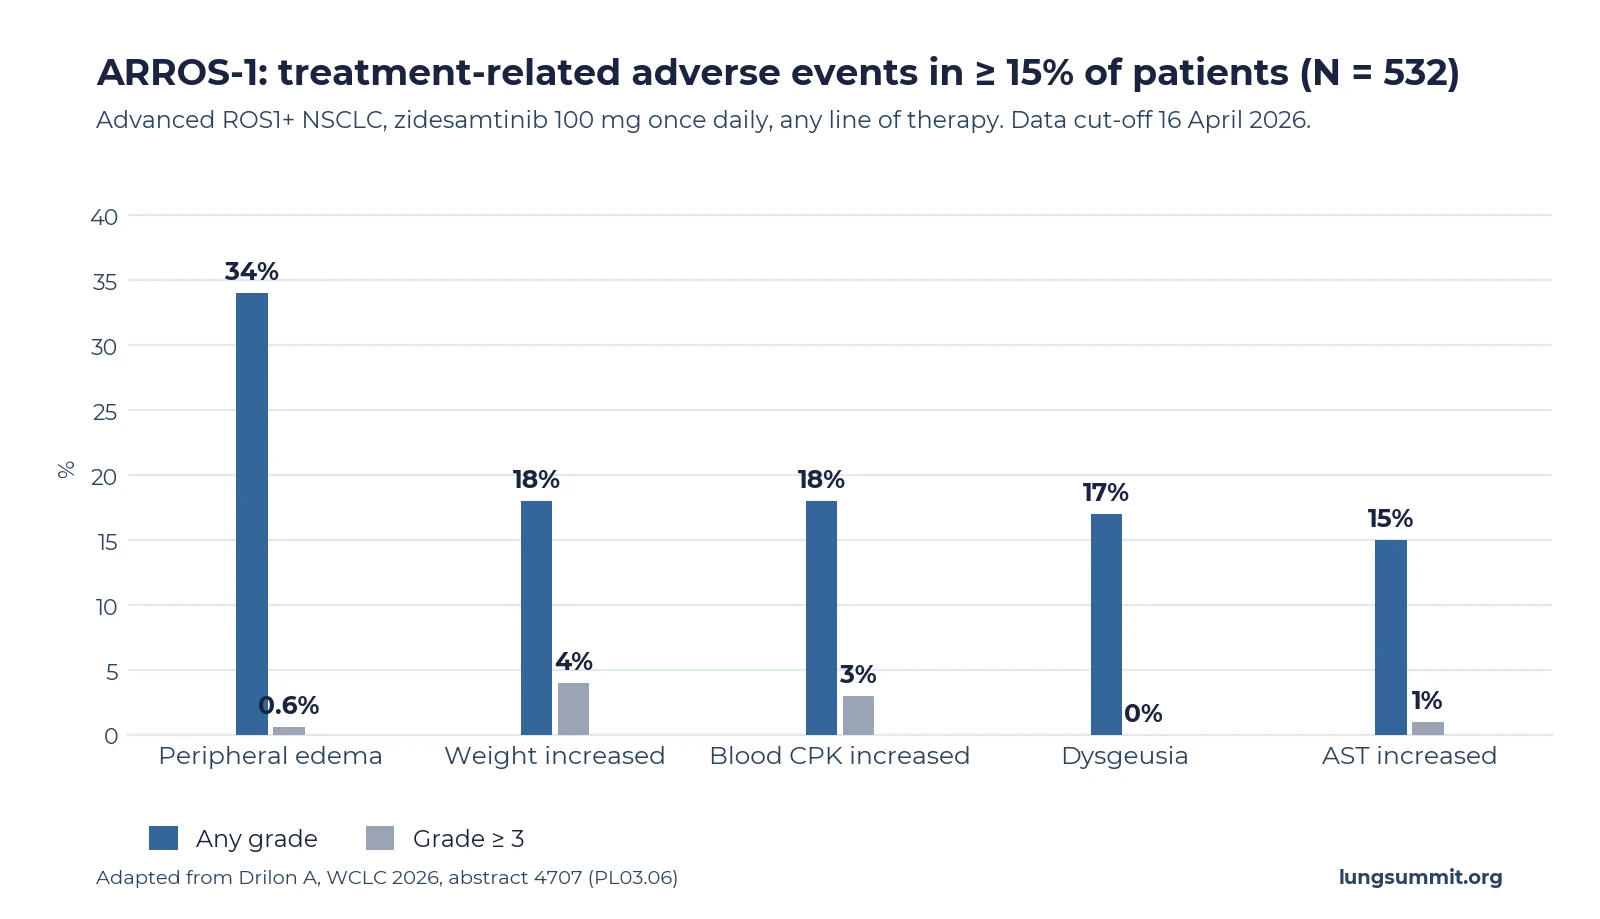
Bar chart of the five most common treatment-related adverse events with zidesamtinib in ARROS-1: peripheral edema 34 percent any grade and 0.6 percent grade 3 or higher, weight increased 18 and 4 percent, blood CPK increased 18 and 3 percent, dysgeusia 17 and 0 percent, AST increased 15 and 1 percent.
Figure 3. Treatment-related adverse events reported in at least 15% of the 532 patients with advanced ROS1+ NSCLC who received zidesamtinib 100 mg once daily in ARROS-1, across all lines of therapy, by any grade and grade 3 or higher. Treatment-related events led to dose reduction in 11% of patients and to discontinuation in 1%. Adapted from Drilon A, WCLC 2026, abstract 4707 (PL03.06).

Dose reductions were made for a treatment-emergent adverse event in 12% of patients and for a treatment-related event in 11%; the events most often responsible were peripheral edema (2.4%), peripheral sensory neuropathy (1.5%), blood CPK increased (1.1%) and weight increased (1.1%). Treatment was discontinued for a treatment-emergent adverse event in 4% of patients and for a treatment-related event in 1%. The events leading to discontinuation in two or more patients were pneumonia (3), pneumonitis (3) and weight increased (2). The presenter described the profile as consistent with the earlier ARROS-1 reports and with the prescribing information.

The IASLC news release carried Dr. Drilon’s summary of the cohort and of what should follow.

“Zidesamtinib demonstrated clinically meaningful activity in TKI-naive patients with ROS1-positive NSCLC, with a safety profile consistent with previous reports and low rates of dose reduction and discontinuation. The findings support continued investigation of zidesamtinib in earlier lines of therapy.”Dr. Alexander Drilon, Memorial Sloan Kettering Cancer Center and Weill Cornell Medical Center, New York, USA

Several limits of the dataset should be kept in view. ARROS-1 is a single-arm trial, so there is no randomised comparison with crizotinib, entrectinib or the other ROS1 TKIs; the response and PFS figures stand on their own. The intracranial analysis rests on 10 patients. Median duration of response and median PFS had not been reached at a median follow-up of 15.2 months, and no survival data were shown. The presentation closed by stating that the data support continued investigation of zidesamtinib as frontline therapy in TKI-naive patients; the drug is not approved in that setting.

Sources

  1. Drilon A, de Langen AJ, Besse B, et al. Zidesamtinib in TKI-naive patients with advanced/metastatic ROS1+ NSCLC: ARROS-1 efficacy and safety data. IASLC 2026 World Conference on Lung Cancer, Seoul, 12–15 September 2026; late-breaking abstract 4707 (session PL03.06).
  2. IASLC news release, Seoul, 14 September 2026: “Zidesamtinib Demonstrates 93% Response Rate in TKI-Naive Patients With Advanced ROS1-Positive NSCLC”.

ILCS 2026

The International Lung Cancer Summit (ILCS 2026) takes place on Friday 13 November 2026 in Lausanne and live online. Faculty will discuss the WCLC 2026 data in the context of daily practice. Register for ILCS 2026 →

Written by the Lung Summit editorial team.

This article was produced independently by the Lung Summit editorial team, without industry funding or input.


i 3 On This Page

Share

       Continue With

Related Topics

Videos
Oliver Gautschi on EGFR+ NSCLC
Jul 20 2026
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Advances in EGFR+ NSCLC: An Interview with Prof. Oliver Gautschi

Prof. Oliver Gautschi discusses recent advances in the treatment of EGFR-mutant non-small cell lung cancer in this on-demand expert interview.

O. Gautschi
Prof. Alessandra Curioni-Fontecedro discussing approaches in metastatic PD-L1 negative NSCLC
May 04 2026
SPONSORED INTERVIEW
Advanced NSCLCImmunotherapies

Approaches in Metastatic PD-L1 Negative NSCLC: An Interview with Prof. Alessandra Curioni-Fontecedro

Prof. Alessandra Curioni-Fontecedro discusses treatment approaches in metastatic PD-L1 negative non-small cell lung cancer in this on-demand expert interview.

A. Curioni-Fontecedro
Lung Cancer Review by Solange Peters, Martin Reck, Charles Rudin
Dec 18 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCSCLCADCs

2025 Approvals & Highlights

} 1 h 49 min

S. PetersC. RudinM. Reck
Sep 26 2025
ILCS 2025
Advanced NSCLC

Latest Options for Non-Oncogene Addicted Advanced NSCLC in Frontline and Beyond

} 32 min

A. Curioni-Fontecedro
Sep 26 2025
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Latest Advances in Frontline EGFR+ NSCLC

} 14 min

A. Curioni-Fontecedro
Sep 26 2025
INDUSTRY SYMPOSIUM
Advanced NSCLCTargeted Therapies

Unlocking New Potentials in EGFR-Mutant NSCLC

} 30 min

A. Passaro
Sep 26 2025
ILCS 2025
Targeted Therapies

DEBATE: Which Is the Better Choice in EGFR+ Advanced NSCLC?

} 31 min

T. Newsom-DavisX. Le
Sep 26 2025
ILCS 2025
Targeted Therapies

Actionable Genomic Alterations – Including HER2 and MET

} 26 min

S. Saw
Sep 26 2025
ILCS 2025
Targeted Therapies

Targeting EGFR and ALK in NSCLC

} 26 min

T. John
Sep 26 2025
ILCS 2025
Advanced NSCLC

Open Discussion on Patient Cases

} 22 min

Targeted Therapies by Oliver Gautschi, Jarushka Naidoo, Nicolas Girard
Jul 10 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCTargeted Therapies

Targeted Therapies in NSCLC

} 1h 30 min

O. GautschiJ. NaidooN. Girard
IO in NSCLC by Solange Peters, Jordi Remon, Patrick Forde
Jun 25 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCImmunotherapies

Immunotherapies in NSCLC

} 1h 47 min

P. FordeJ. RemonS. Peters
Girard ADCs
Oct 05 2024
INDUSTRY SYMPOSIUM
Advanced NSCLCADCs

Best Practices in Managing Adverse Events with ADCs in NSCLC

} 18 min

N. Girard
Patient Cases
Oct 04 2024
ILCS 2024
Advanced NSCLCResectable NSCLC

Patient Cases & Open Questions

} 32 min

Sandip Patel & Giannis Mountzios
Oct 04 2024
ILCS 2024
Advanced NSCLC

DEBATE: Balancing Efficacy, Toxicity, and Patient-Centered Care For IO Duration in NSCLC

} 33 min

G. MountziosS. Patel
Biagio Ricciuti
Oct 04 2024
ILCS 2024
Targeted Therapies

Decoding Actionable Alterations: Insights from KRAS, HER2, and c-MET

} 25 min

B. Ricciuti
Roberto Ferrara
Oct 04 2024
ILCS 2024
Targeted Therapies

Rare But Actionable: How To Target for RET, METex14 and NTRK

} 20 min

R. Ferrara
Anne-Marie Dingemans
Oct 04 2024
ILCS 2024
Targeted Therapies

Current Options in Targeting EGFR and ALK Beyond Osimertinib and Alectinib

} 25 min

A. Dingemans
Nov132026
ILCS 2026

The International Lung Cancer Summit 2026

Learn more about the event

S. PetersA. AddeoM. DasH. HorinouchiT. SequeiraC. LovlyD. PlanchardS. PatelA. CortelliniN. FrostG. MountziosA. Dingemans
Oct252026
ESMO 2026 SYMPOSIUM
SCLC

SCLC Symposium at ESMO 2026: From IO-Standards to the TCE Era

Learn more about the event

M. ReckS. PetersG. MountziosN. Reguart
Articles
Oct 14 2026
RESEARCH
Advanced NSCLCTargeted Therapies

Durable responders to immunotherapy for NSCLC or melanoma mostly reported good health, but frequent fatigue

N. Girard
Oct 08 2026
RESEARCH
Advanced NSCLCTargeted Therapies

Amivantamab, lazertinib and bevacizumab gave a 33% response rate after osimertinib in AMAZE-lung

R. StahelM. PérolA. AddeoS. Peters
Oct 06 2026
RESEARCH
Advanced NSCLCImmunotherapies

Two-thirds of patients with PD-L1-high NSCLC received first-line immunotherapy alone in a real-world survey

D. Rodríguez-Abreu
Alfredo Addeo
Oct 05 2026
RESEARCH
Advanced NSCLCTargeted Therapies

A JCO review sets PACC mutations and exon 20 insertions apart from classical EGFR mutations in NSCLC

A. AddeoX. Le
Nikolaj Frost
Oct 04 2026
RESEARCH
Advanced NSCLCSCLCTargeted Therapies

Checkpoint inhibitors were associated with longer survival in NSCLC after allogeneic stem cell transplantation

N. FrostM. ReckA. Cortellini
Oct 03 2026
RESEARCH
Advanced NSCLCResectable NSCLCTargeted Therapies

AI-extracted records describe stage I–III NSCLC care at four Spanish hospitals before immunotherapy

A. Calles
Oct 03 2026
RESEARCH
Advanced NSCLCTargeted Therapies

KRAS inhibitors in NSCLC: modest survival gains, inevitable resistance and combinations in early trials

V. Noronha
Oct 02 2026
RESEARCH
Advanced NSCLCTargeted Therapies

Sutetinib produced responses in 71% of patients with uncommon EGFR mutations in a phase IIb trial

X. Le
Oct 02 2026
RESEARCH
Advanced NSCLCBiomarkersImmunotherapies

High tumour mutational burden was associated with more frequent and earlier immune-related adverse events in advanced NSCLC

B. Ricciuti
Oct 01 2026
RESEARCH
Advanced NSCLCTargeted Therapies

Uncommon EGFR exon 19 deletions were associated with shorter PFS on osimertinib in a 111-patient study

H. Horinouchi
Oct 01 2026
RESEARCH
Targeted Therapies

RAS alterations drove resistance in about one in ten oncogene-driven lung cancers progressing on targeted therapy

B. RicciutiJ. RemonD. Planchard
Sep 30 2026
RESEARCH
Advanced NSCLCSCLCADCs

Pulmonary adverse events affected almost a third of lung cancer patients treated with ADCs in a 24-study meta-analysis

C. Rolfo
Sep 26 2026
RESEARCH
Advanced NSCLCImmunotherapies

Incidental thymic radiation dose was independently associated with metastasis and death in 1107 patients with NSCLC

B. Ricciuti
Sep 25 2026
RESEARCH
Resectable NSCLCTargeted Therapies

Multi-omic profiling separated recurrence risk within pathological stage in resected EGFR-mutant lung adenocarcinoma

S. Saw
Portrait of Dr. Alexander Drilon
Sep 23 2026
CONGRESS
Advanced NSCLCTargeted Therapies

Zidesamtinib produced responses in 94% of ROS1 TKI-naive patients in ARROS-1

Sep 18 2026
INDUSTRY NEWS
Advanced NSCLCTargeted Therapies

Sevabertinib approved in the US for untreated HER2-mutant NSCLC

Sep 17 2026
CONGRESS
Resectable NSCLCTargeted Therapies

Adjuvant osimertinib reduced the risk of death by 47% at eight years in ADAURA

Sep 17 2026
RESEARCH
Advanced NSCLCTargeted Therapies

Grade 3 adverse events on the FLAURA2 combination fell from 43% during induction to 14% on osimertinib alone

D. Planchard
Sep 16 2026
CONGRESS
Advanced NSCLCADCs

First-line trastuzumab deruxtecan extended median PFS to 14.3 months in HER2-mutant NSCLC

Sep 16 2026
CONGRESS
SCLCTargeted Therapies

Tam-Peli extended median OS to 13.3 months in relapsed SCLC, against 9.4 months with topotecan