SELECT FROM MENU

Therapy Areas
Drug Classes

       Therapy Areas

All Sessions

All Sessions

Resectable NSCLC

Resectable NSCLC

Advanced NSCLC

Advanced NSCLC

SCLC

SCLC

Biomarkers

Biomarkers

       Drug Classes

Targeted Therapies

Targeted Therapies

Immunotherapies

Immunotherapies

ADCs

ADCs

BiomarkersAugust 13, 2026

Pre-surgical ctDNA clearance reached 66% with neoadjuvant nivolumab against 38% with placebo in CheckMate 77T

Circulating tumour DNA cleared before surgery in two thirds of the CheckMate 77T patients who received neoadjuvant nivolumab and had evaluable samples, and in just over a third of the comparable placebo group, according to a biomarker analysis published in Nature. The same analysis reports that clearance occurred alongside pathologic complete response, that a return of molecular residual disease during adjuvant treatment was followed by recurrence in every case recorded, and that patients whose tumours carried alterations in four driver genes appeared to derive event-free survival benefit from nivolumab.
Share

In brief

  • In the biomarker analysis of CheckMate 77T, 50 of 76 patients (66%) given neoadjuvant nivolumab cleared circulating tumour DNA before surgery, against 24 of 64 (38%) given placebo.
  • Of the 50 nivolumab-treated patients who cleared ctDNA, 25 (50%) had a pathologic complete response; of the 24 placebo-treated patients who cleared it, 3 (12%) did.
  • Every patient whose molecular residual disease turned positive during the adjuvant period had disease recurrence: 4 of 48 (8%) in the nivolumab group and 9 of 44 (20%) in the placebo group.
  • In patients carrying alterations in KEAP1, STK11, CDKN2A or SMARCA4, event-free survival with nivolumab (n=60) against placebo (n=45) gave a hazard ratio of 0.48 (95% CI 0.28 to 0.83).
  • The analysis covers 190 of 461 randomised patients, or 41% of the trial, so every figure here describes a biomarker-evaluable subset rather than the randomised population.

Study at a glance

  • Cohort: CheckMate 77T (ClinicalTrials.gov NCT04025879), biomarker analysis
  • Population: Resectable non-small cell lung cancer; 98 of 229 nivolumab-assigned and 92 of 232 placebo-assigned patients had evaluable biomarkers (41% of those randomised)
  • Treatment: Perioperative nivolumab against placebo
  • ctDNA detectable at baseline: 83 of 98 (85%) with nivolumab; 75 of 92 (82%) with placebo
  • Pre-surgical ctDNA clearance: 50 of 76 (66%) with nivolumab; 24 of 64 (38%) with placebo
  • Pathologic complete response after clearance: 25 of 50 (50%) with nivolumab; 3 of 24 (12%) with placebo
  • Driver-gene subgroup: KEAP1, STK11, CDKN2A or SMARCA4 alterations, hazard ratio 0.48 (95% CI 0.28 to 0.83) for event-free survival
  • Not reported in the abstract: Median event-free survival in either arm of the biomarker subset, and any survival figure for the ctDNA-clearance comparison

Pre-surgical ctDNA clearance in 66% of evaluable nivolumab patients against 38% on placebo

Among the 98 nivolumab-treated patients with evaluable biomarkers, 76 (78%) had detectable and evaluable circulating tumour DNA both before and after neoadjuvant treatment, and 50 of those 76 (66%) cleared it before surgery. In the placebo group, 64 of 92 patients (70%) met the same evaluability condition, and 24 of them (38%) cleared it.

The denominators matter for reading those percentages. Clearance is only measurable in a patient whose ctDNA was detectable to begin with and whose post-treatment sample could be evaluated, so the 66% and the 38% describe 76 and 64 patients respectively, not the 229 and 232 who were randomised. Detection at baseline itself was not universal: 83 of 98 nivolumab-treated patients (85%) and 75 of 92 placebo-treated patients (82%) had detectable ctDNA before neoadjuvant treatment began, and detection rose to 90 of 98 (92%) and 78 of 92 (85%) at the completion of neoadjuvant treatment.

Half of the nivolumab patients who cleared ctDNA had a pathologic complete response

Of the 50 nivolumab-treated patients with pre-surgical clearance, 25 (50%) had a pathologic complete response at surgery. Of the 24 placebo-treated patients with clearance, 3 (12%) did.

The two measures are taken at different moments and from different material. Clearance is a blood measurement made before the operation, and pathologic complete response is read from the resection specimen afterwards, so the second is a check on what the first anticipated. What the figures establish is that clearance and pathologic complete response occurred together far more often in the nivolumab group, and that clearance on placebo was much less likely to be accompanied by a complete pathologic result. The abstract carries no survival figure attached to either comparison.

Every patient whose molecular residual disease returned during adjuvant treatment relapsed

Four of 48 patients (8%) in the nivolumab group and 9 of 44 (20%) in the placebo group were negative for molecular residual disease after surgery and before adjuvant treatment began, then turned positive during the adjuvant period. All of them had disease recurrence.

Thirteen patients is a small number on which to rest a statement about a test, and the analysis reports the observation rather than a predictive value derived from it. The finding is nevertheless unambiguous within its own cohort: in this trial, no patient who converted from molecular residual disease negative to positive on adjuvant treatment avoided recurrence.

“These findings provide insights into predictive markers for outcomes with perioperative nivolumab in resectable NSCLC.”Cascone et al., Nature (2026)

A hazard ratio of 0.48 in tumours carrying KEAP1, STK11, CDKN2A or SMARCA4 alterations

Event-free survival appeared prolonged with nivolumab (n=60) against placebo (n=45) in patients whose tumours carried single alterations or co-alterations in any of KEAP1, STK11, CDKN2A or SMARCA4, with a hazard ratio of 0.48 and a 95% confidence interval of 0.28 to 0.83. The authors report the result with the verb “seemed”, and the abstract gives no median event-free survival for either arm of that subgroup.

A machine-learning model trained on the biomarker-evaluable patients placed pre-surgical ctDNA clearance, non-N2 disease, pathologic complete response, squamous histology and nivolumab treatment among its top predictors of prolonged event-free survival. The abstract names those predictors without ordering them and gives no performance measure for the model itself.

The analysis covers 41% of the randomised patients

Biomarkers were evaluable in 98 of 229 patients assigned to nivolumab and 92 of 232 assigned to placebo, which the authors state is 41% of those randomised. Every figure above is therefore drawn from patients who had usable samples, and the analysis does not establish that they resemble the 59% who did not.

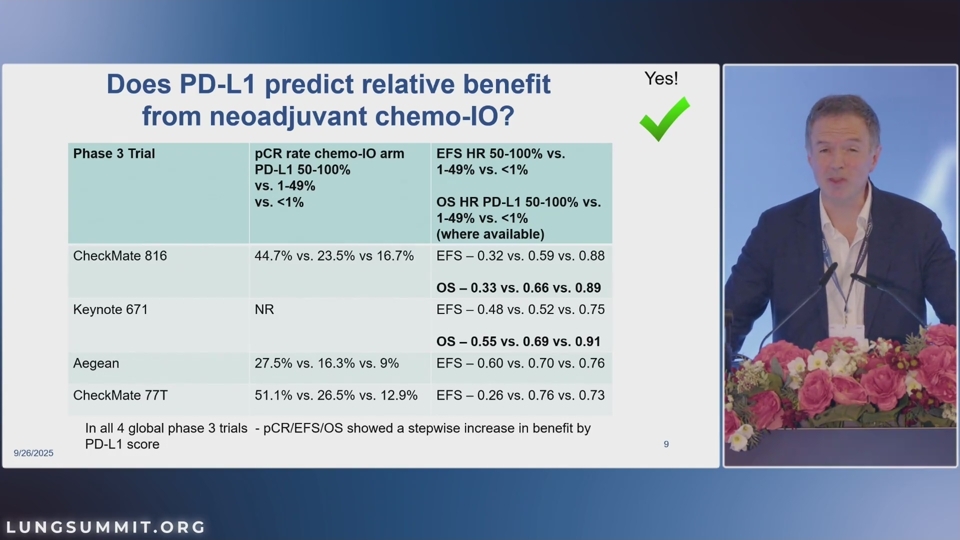
CheckMate 77T reported previously that perioperative nivolumab significantly improved event-free survival against placebo in resectable non-small cell lung cancer. This report does not revisit that primary result. It describes which patients within the trial the benefit tracked with, on samples collected during the trial, and the strength of the evidence is that of a biomarker analysis of a subset rather than of a randomised comparison.

Sources

  1. Nature. Biomarkers of nivolumab benefit in resectable non-small cell lung cancer (2026-08-12). doi.org

Featuring Lung Summit faculty

This study was co-authored by Lung Summit faculty Tina Cascone.

This article was produced independently by the Lung Summit editorial team, without industry funding or input.

i 3 On This Page

Share

       Continue With

Related Topics

Videos
Prof. Alessandra Curioni-Fontecedro discussing approaches in metastatic PD-L1 negative NSCLC
May 04 2026
SPONSORED INTERVIEW
Advanced NSCLCImmunotherapies

Approaches in Metastatic PD-L1 Negative NSCLC: An Interview with Prof. Alessandra Curioni-Fontecedro

Prof. Alessandra Curioni-Fontecedro discusses treatment approaches in metastatic PD-L1 negative non-small cell lung cancer in this on-demand expert interview.

A. Curioni-Fontecedro
Lung Cancer Review by Solange Peters, Martin Reck, Charles Rudin
Dec 18 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCSCLCADCs

2025 Approvals & Highlights

} 1 h 49 min

S. PetersC. RudinM. Reck
Sep 26 2025
ILCS 2025
Immunotherapies

The Role of IO Added to Chemoradiation in Unresectable Stage III NSCLC

} 28 min

A. Filippi
Sep 26 2025
ILCS 2025
Immunotherapies

Tailoring IO in Res. NSCLC: Personalized Approaches for Improved Outcomes

} 36 min

P. Forde
Sep 26 2025
ILCS 2025
Biomarkers

Cutting-Edge Diagnostic Techniques and Emerging Biomarkers

} 24 min

M. Ilié
IO in NSCLC by Solange Peters, Jordi Remon, Patrick Forde
Jun 25 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCImmunotherapies

Immunotherapies in NSCLC

} 1h 47 min

P. FordeJ. RemonS. Peters
SCLC by Solange Peters, Giannis Mountzios, Jacob Sands
Jun 17 2025
VIRTUAL ROUNDTABLE
SCLCImmunotherapies

Small Cell Lung Cancer

} 1h 35 min

G. MountziosJ. SandsS. Peters
Patient Cases
Oct 04 2024
ILCS 2024
Advanced NSCLCResectable NSCLC

Patient Cases & Open Questions

} 32 min

Jordi Remon
Oct 04 2024
ILCS 2024
Immunotherapies

Tailoring IO in Resectable NSCLC: Personalized Approaches for Improved Outcomes

} 25 min

J. Remon
Nuria Maria Novoa
Oct 04 2024
ILCS 2024
Resectable NSCLC

Surgical Dilemmas: Defining Resectability for Optimal Patient Outcomes in the IO Era

} 27 min

N. Novoa
Anne Schultheis
Oct 04 2024
ILCS 2024
Biomarkers

Advancements in Diagnostics: Current Guidelines and Emerging Tests

} 20 min

A. Schultheis
Oliver Gautschi on EGFR+ NSCLC
Jul 20 2026
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Advances in EGFR+ NSCLC: An Interview with Prof. Oliver Gautschi

Prof. Oliver Gautschi discusses recent advances in the treatment of EGFR-mutant non-small cell lung cancer in this on-demand expert interview.

O. Gautschi
Oct252026
ESMO 2026 SYMPOSIUM
SCLC

SCLC Symposium at ESMO 2026: From IO-Standards to the TCE Era

Learn more about the event

M. ReckS. PetersG. MountziosN. Reguart
Nov132026
ILCS 2026

The International Lung Cancer Summit 2026

Learn more about the event

S. PetersA. AddeoM. DasH. HorinouchiT. SequeiraC. LovlyD. PlanchardS. PatelA. CortelliniN. FrostG. MountziosA. Dingemans
Sep 26 2025
ILCS 2025
SCLC

Reshaping Approaches in SCLC with the Latest Advances in LS- and ES-Disease

} 34 min

R. Manochakian
Sep 26 2025
ILCS 2025
Advanced NSCLC

Latest Options for Non-Oncogene Addicted Advanced NSCLC in Frontline and Beyond

} 32 min

A. Curioni-Fontecedro
Sep 26 2025
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Latest Advances in Frontline EGFR+ NSCLC

} 14 min

A. Curioni-Fontecedro
Sep 26 2025
INDUSTRY SYMPOSIUM
Advanced NSCLCTargeted Therapies

Unlocking New Potentials in EGFR-Mutant NSCLC

} 30 min

A. Passaro
Sep 26 2025
ILCS 2025
ADCs

The ADC Revolution in Lung Cancer: New Targets, New Opportunities

} 27 min

N. Reguart
Sep 26 2025
ILCS 2025
Targeted Therapies

DEBATE: Which Is the Better Choice in EGFR+ Advanced NSCLC?

} 31 min

T. Newsom-DavisX. Le
Articles
Oct 14 2026
RESEARCH
Resectable NSCLC

More lymph nodes examined at segmentectomy tracked with longer survival in early-stage NSCLC

J. Perentes
Oct 07 2026
RESEARCH
BiomarkersSCLC

IASLC pathologists propose a grade 3 category for lung carcinoids with more than 10 mitoses

P. Hofman
Oct 06 2026
RESEARCH
Advanced NSCLCImmunotherapies

Two-thirds of patients with PD-L1-high NSCLC received first-line immunotherapy alone in a real-world survey

D. Rodríguez-Abreu
Oct 05 2026
RESEARCH
SCLCImmunotherapies

Second-line therapy in ES-SCLC gave a median OS of 7.1 months in the Austrian LALUCA registry

M. Hochmair
Oct 04 2026
RESEARCH
SCLCImmunotherapies

Longer OS in Asian than non-Asian patients given atezolizumab plus chemotherapy for extensive-stage SCLC

S. LiuM. ReckC. Rudin
Oct 03 2026
RESEARCH
Advanced NSCLCResectable NSCLCTargeted Therapies

AI-extracted records describe stage I–III NSCLC care at four Spanish hospitals before immunotherapy

A. Calles
Oct 02 2026
RESEARCH
Advanced NSCLCBiomarkersImmunotherapies

High tumour mutational burden was associated with more frequent and earlier immune-related adverse events in advanced NSCLC

B. Ricciuti
Sep 30 2026
RESEARCH
Resectable NSCLC

Spread through air spaces predicted relapse after both lobectomy and segmentectomy in JCOG0802 stage IA NSCLC

S. BerezowskaL. BubendorfP. Hofman
Martin Reck
Sep 28 2026
RESEARCH
Resectable NSCLCImmunotherapies

AEGEAN’s second interim analysis kept the EFS benefit of perioperative durvalumab, on an OS reading that crosses 1

M. ReckM. Hochmair
Sep 26 2026
RESEARCH
Advanced NSCLCImmunotherapies

Incidental thymic radiation dose was independently associated with metastasis and death in 1107 patients with NSCLC

B. Ricciuti
Sep 25 2026
RESEARCH
Resectable NSCLCTargeted Therapies

Multi-omic profiling separated recurrence risk within pathological stage in resected EGFR-mutant lung adenocarcinoma

S. Saw
Sep 19 2026
RESEARCH
Resectable NSCLC

Spread through air spaces carried an HR of 2.32 for DFS in stage 1 lung adenocarcinoma

S. Saw
Sep 17 2026
CONGRESS
Resectable NSCLCTargeted Therapies

Adjuvant osimertinib reduced the risk of death by 47% at eight years in ADAURA

Sep 15 2026
CONGRESS
Advanced NSCLCImmunotherapies

HARMONi-2: ivonescimab extends overall survival over pembrolizumab in China

Sep 15 2026
CONGRESS
Advanced NSCLCBiomarkersResectable NSCLC

WCLC 2026, day 4: tumour budding, BRAF class II and III, brain radiotherapy timing, and mobile CT screening

Sep 14 2026
CONGRESS
Advanced NSCLCResectable NSCLCADCs

WCLC 2026, day 3: EGFR exon 20, ROS1 and HER2 in advanced NSCLC, and 79% alive at eight years after surgery

Sep 14 2026
CONGRESS
Resectable NSCLCTargeted Therapies

ADAURA at eight years: adjuvant osimertinib keeps a 15-point overall survival lead

Sep 13 2026
CONGRESS
Advanced NSCLCSCLCADCs

WCLC 2026, day 2: MRI surveillance without prophylactic cranial irradiation, and two relapse trials at 13.3 and 18.5 months

Giannis Mountzios
Sep 13 2026
CONGRESS
Advanced NSCLCADCsImmunotherapies

EVOKE-03: sacituzumab govitecan plus pembrolizumab misses both primary endpoints

G. Mountzios
Sep 12 2026
CONGRESS
Advanced NSCLCResectable NSCLCSCLC

WCLC 2026, day 1: extended-interval and subcutaneous dosing in SCLC, and a 70% early response