In brief
- At a second planned interim analysis, event-free survival continued to favour perioperative durvalumab, with a hazard ratio of 0.69 (95% CI 0.55 to 0.88) in the 740-patient modified intention-to-treat population.
- Interim disease-free survival in the resected subpopulation gave a hazard ratio of 0.66 (95% CI 0.47 to 0.92), reported as a numerical improvement.
- Interim overall survival gave a hazard ratio of 0.89 (95% CI 0.70 to 1.14), favouring durvalumab numerically on a confidence interval that crosses 1.
- Maximum grade 3/4 adverse events during adjuvant treatment occurred in 15.4% of the durvalumab arm and 10.6% of the placebo arm.
- The data cut-off was 10 May 2024, at a median follow-up of 25.9 months in censored patients, after all patients had completed or discontinued treatment.
Study at a glance
- Trial: AEGEAN, phase III, double-blind, placebo-controlled, randomised 1:1
- Population: treatment-naïve resectable NSCLC, stage II to IIIB (N2), with documented EGFR or ALK aberrations excluded from the efficacy analysis
- Cohort analysed: modified intention-to-treat population, n = 740, and its resected subpopulation for disease-free survival
- Treatment: neoadjuvant platinum-based chemotherapy with durvalumab or placebo every 3 weeks for four cycles before surgery, then durvalumab or placebo every 4 weeks for 12 cycles after it
- Follow-up: data cut-off 10 May 2024, median 25.9 months in censored patients
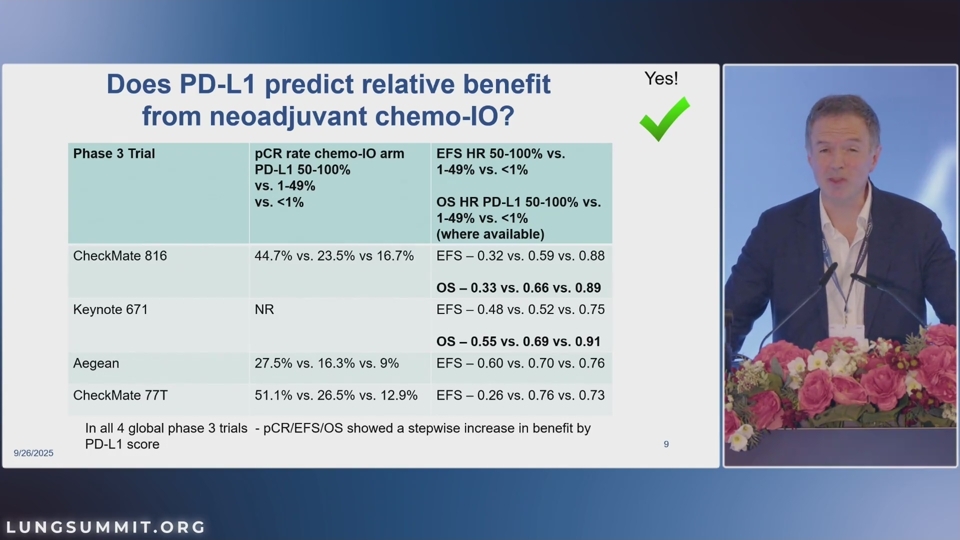
- Event-free survival: HR 0.69 (95% CI 0.55 to 0.88), second planned interim analysis
- Disease-free survival: HR 0.66 (95% CI 0.47 to 0.92), interim
- Overall survival: HR 0.89 (95% CI 0.70 to 1.14), interim
- Not reported: the abstract gives no median event-free, disease-free or overall survival in months, no pathological complete response figures at this cut-off, and no size for the resected subpopulation
An event-free survival hazard ratio of 0.69 at the second planned interim analysis
The reading was taken after all patients had completed or discontinued study treatment, in the modified intention-to-treat population of 740, and the confidence interval ran from 0.55 to 0.88.
The comparison behind that figure is perioperative durvalumab against neoadjuvant chemotherapy alone, and event-free survival is one of the two endpoints on which AEGEAN was first reported, alongside pathological complete response. Event-free survival counts events from randomisation, which means it captures the patient whose disease progressed before an operation could happen as well as the patient who relapsed after one. The efficacy population excludes patients with documented EGFR or ALK aberrations, so the hazard ratio describes a population from which documented EGFR-driven and ALK-driven disease has been removed.
Disease-free survival in the resected subpopulation gave a hazard ratio of 0.66
That analysis covers only the patients who reached surgery, a group selected after randomisation rather than by it, and the authors report the result as interim and as a numerical improvement.
The distinction between the two endpoints matters, because disease-free survival is measured in a subset of the population event-free survival is measured in, and membership of that subset is decided after randomisation by whether surgery happened. A patient whose disease progressed beforehand contributes an event to event-free survival and never enters the resected subpopulation at all. The two numbers sit close to each other here, 0.69 and 0.66, and they are answering different questions.
An overall survival hazard ratio of 0.89, on a confidence interval that crosses 1
Interim overall survival favoured the durvalumab arm numerically, and at 0.70 to 1.14 the interval is compatible with a moderate survival benefit and with a small disadvantage alike.
A median follow-up of 25.9 months is short for survival in resectable disease. Patients in both arms may live for years after treatment, and the curves need time before they can separate. The authors present the figure as interim, which is the right weight for it, and an interim reading at this cut-off is a checkpoint rather than an answer.
“These results further support perioperative durvalumab plus neoadjuvant chemotherapy as a new treatment option.”Heymach et al., Journal of Clinical Oncology (2026)
Maximum grade 3/4 adverse events in the adjuvant phase, 15.4% against 10.6%
That comparison is confined to the period after surgery, when one arm receives durvalumab, the other receives placebo, and the platinum chemotherapy is behind both of them, so neither rate includes a patient on concurrent chemotherapy.
The gap is just under five percentage points. It is the figure that speaks most directly to what the perioperative design asks of somebody who has already had a lung resection and four cycles of platinum chemotherapy, which is twelve further cycles at four-weekly intervals, running close to a year. Earlier AEGEAN reporting described the safety profile as consistent with the individual agents, and these adjuvant-phase rates are what this update adds to that picture.
Sources
- Journal of Clinical Oncology. Perioperative Durvalumab for Resectable Non–Small Cell Lung Cancer: Updated Outcomes From the Phase III AEGEAN Trial (2026-08-28). doi.org
Featuring Lung Summit faculty
This study was co-authored by Lung Summit faculty Martin Reck and Maximilian Hochmair.
This article was produced independently by the Lung Summit editorial team, without industry funding or input.