SELECT FROM MENU

Therapy Areas
Drug Classes

       Therapy Areas

All Sessions

All Sessions

Resectable NSCLC

Resectable NSCLC

Advanced NSCLC

Advanced NSCLC

SCLC

SCLC

Biomarkers

Biomarkers

       Drug Classes

Targeted Therapies

Targeted Therapies

Immunotherapies

Immunotherapies

ADCs

ADCs

Resectable NSCLCAugust 2, 2026

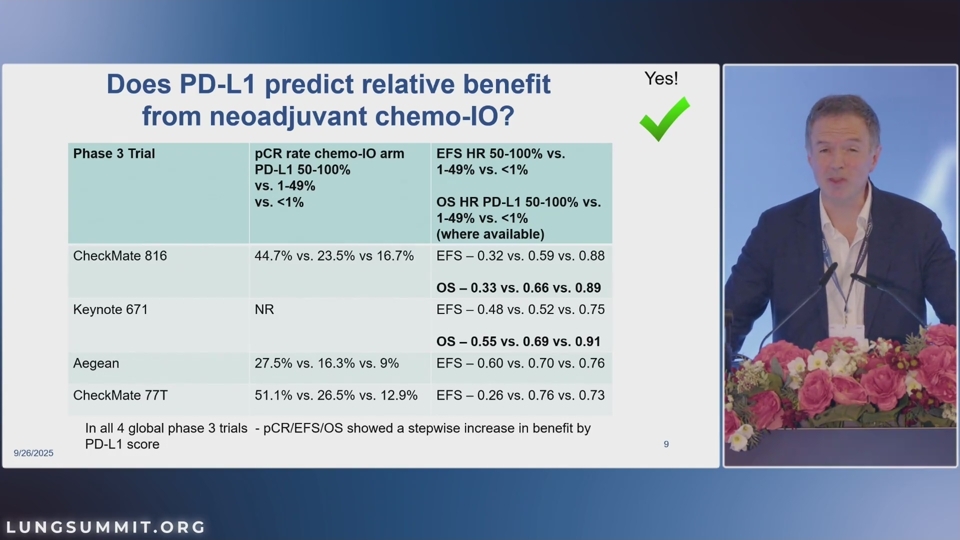
Five-year event-free survival was 49.9% with perioperative pembrolizumab against 26.5% in KEYNOTE-671

Adding pembrolizumab to neoadjuvant chemotherapy and continuing it after surgery left half of patients with resectable non-small cell lung cancer event free at five years, against just over a quarter of patients given chemotherapy and surgery alone, according to the five-year analysis of the phase 3 KEYNOTE-671 trial published in Annals of Oncology. Overall survival, the trial's other primary endpoint, was 64.6% against 53.6% at the same timepoint.
Share

In brief

  • At five years, event-free survival in KEYNOTE-671 was 49.9% (95% CI 44.6 to 55.0) with perioperative pembrolizumab and 26.5% (21.7 to 31.5) with placebo, a hazard ratio of 0.58 (0.48 to 0.69).
  • Five-year overall survival was 64.6% (59.5 to 69.2) against 53.6% (48.3 to 58.6), a hazard ratio of 0.74 (0.59 to 0.92).
  • 797 patients with previously untreated, resectable stage II, IIIA or IIIB (N2) NSCLC were randomised, 397 to pembrolizumab and 400 to placebo.
  • Median time from randomisation to the 3 July 2025 data cutoff was 60.4 months, with a range of 42.6 to 85.8 months.
  • No detriment to health-related quality of life was identified with the longer follow-up, and safety was consistent with the known profiles of each treatment.

Study at a glance

  • Cohort: KEYNOTE-671 (ClinicalTrials.gov NCT03425643), phase 3, randomised, 797 participants
  • Population: Previously untreated, resectable stage II, IIIA or IIIB (N2) non-small cell lung cancer
  • Treatment: Four cycles of pembrolizumab 200 mg or placebo every three weeks with platinum-doublet chemotherapy, then surgery, then pembrolizumab or placebo every three weeks for up to 13 cycles
  • Primary endpoints: Event-free survival by RECIST v1.1 investigator assessment, and overall survival
  • Follow-up: Median 60.4 months from randomisation to the 3 July 2025 cutoff (range 42.6 to 85.8)
  • Five-year event-free survival: 49.9% against 26.5% (hazard ratio 0.58, 95% CI 0.48 to 0.69)
  • Five-year overall survival: 64.6% against 53.6% (hazard ratio 0.74, 95% CI 0.59 to 0.92)
  • Not reported in the abstract: Median event-free or overall survival in either arm, and any subgroup result

Five-year event-free survival of 49.9% against 26.5%

Half of the patients randomised to perioperative pembrolizumab were alive without an event at five years. In the placebo group the figure was 26.5%. The hazard ratio of 0.58, with a 95% confidence interval from 0.48 to 0.69, does not cross 1, and the confidence intervals around the two five-year rates (44.6 to 55.0 and 21.7 to 31.5) do not overlap.

Event-free survival here was assessed by the investigator using RECIST v1.1, which the authors state in the methods, and it is one of two primary endpoints rather than a secondary measure. Overall survival is the other, so both of the trial’s primary questions are answered in this report at the same cutoff.

An 11 percentage point difference in five-year overall survival

Overall survival at five years was 64.6% with pembrolizumab and 53.6% with placebo, a hazard ratio of 0.74 with a 95% confidence interval from 0.59 to 0.92. The interval excludes 1, and the separation the authors describe as continuing represents 11 percentage points at the five-year mark.

The overall survival difference is smaller in proportional terms than the event-free survival difference. Event-free survival ran at 49.9% against 26.5%, a ratio of about 1.9, while overall survival ran at 64.6% against 53.6%, a ratio of about 1.2. The abstract records no data on what patients received after recurrence, so what lies behind that narrowing cannot be read from it.

“After 5 years of follow-up, EFS was nearly double with perioperative pembrolizumab plus neoadjuvant chemotherapy, along with continued improvement in OS compared with neoadjuvant chemotherapy and surgery alone.”Wakelee et al., Annals of Oncology (2026)

A median 60.4 months of follow-up, in a range running from 42.6 to 85.8

Median time from randomisation to the data cutoff of 3 July 2025 was 60.4 months, and the range ran from 42.6 to 85.8 months. The lower end of that range matters to the reading of a five-year rate: the patients randomised latest had been followed for 42.6 months at the cutoff, which is short of five years, so not every participant contributed observed follow-up to the five-year timepoint.

Patients received four cycles of pembrolizumab 200 mg or placebo every three weeks with platinum-doublet chemotherapy, then surgery, then up to 13 cycles of pembrolizumab or placebo every three weeks. Randomisation was 1:1, and 797 patients were assigned, 397 to pembrolizumab and 400 to placebo.

No quality-of-life detriment, and safety consistent with the known profiles

The authors report that no detriment to health-related quality of life was identified in the pembrolizumab arm against the placebo arm with the longer follow-up, and that safety was consistent with the known profiles of each treatment. The abstract carries no adverse event rates, no instrument name for the quality-of-life assessment and no timepoints for it.

On these results the authors state that the durable and clinically meaningful benefits observed support use of this treatment as a standard of care for patients with resectable early-stage non-small cell lung cancer. That sentence is the authors’ own conclusion rather than a finding, and it rests on the two five-year rates and the quality-of-life and safety statements above.

Sources

  1. Annals of Oncology. Five-Year Outcomes of Perioperative Pembrolizumab for Early-Stage Non–Small-Cell Lung Cancer From the Randomized KEYNOTE-671 Study (2026-08-01). doi.org

Featuring Lung Summit faculty

This study was co-authored by Lung Summit faculty Delvys Rodríguez-Abreu and Martin Reck.

This article was produced independently by the Lung Summit editorial team, without industry funding or input.

i 3 On This Page

Share

       Continue With

Related Topics

Videos
Prof. Alessandra Curioni-Fontecedro discussing approaches in metastatic PD-L1 negative NSCLC
May 04 2026
SPONSORED INTERVIEW
Advanced NSCLCImmunotherapies

Approaches in Metastatic PD-L1 Negative NSCLC: An Interview with Prof. Alessandra Curioni-Fontecedro

Prof. Alessandra Curioni-Fontecedro discusses treatment approaches in metastatic PD-L1 negative non-small cell lung cancer in this on-demand expert interview.

A. Curioni-Fontecedro
Lung Cancer Review by Solange Peters, Martin Reck, Charles Rudin
Dec 18 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCSCLCADCs

2025 Approvals & Highlights

} 1 h 49 min

S. PetersC. RudinM. Reck
Sep 26 2025
ILCS 2025
Immunotherapies

The Role of IO Added to Chemoradiation in Unresectable Stage III NSCLC

} 28 min

A. Filippi
Sep 26 2025
ILCS 2025
Immunotherapies

Tailoring IO in Res. NSCLC: Personalized Approaches for Improved Outcomes

} 36 min

P. Forde
IO in NSCLC by Solange Peters, Jordi Remon, Patrick Forde
Jun 25 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCImmunotherapies

Immunotherapies in NSCLC

} 1h 47 min

P. FordeJ. RemonS. Peters
SCLC by Solange Peters, Giannis Mountzios, Jacob Sands
Jun 17 2025
VIRTUAL ROUNDTABLE
SCLCImmunotherapies

Small Cell Lung Cancer

} 1h 35 min

G. MountziosJ. SandsS. Peters
Patient Cases
Oct 04 2024
ILCS 2024
Advanced NSCLCResectable NSCLC

Patient Cases & Open Questions

} 32 min

Jordi Remon
Oct 04 2024
ILCS 2024
Immunotherapies

Tailoring IO in Resectable NSCLC: Personalized Approaches for Improved Outcomes

} 25 min

J. Remon
Nuria Maria Novoa
Oct 04 2024
ILCS 2024
Resectable NSCLC

Surgical Dilemmas: Defining Resectability for Optimal Patient Outcomes in the IO Era

} 27 min

N. Novoa
Oliver Gautschi on EGFR+ NSCLC
Jul 20 2026
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Advances in EGFR+ NSCLC: An Interview with Prof. Oliver Gautschi

Prof. Oliver Gautschi discusses recent advances in the treatment of EGFR-mutant non-small cell lung cancer in this on-demand expert interview.

O. Gautschi
Nov132026
ILCS 2026

The International Lung Cancer Summit 2026

Learn more about the event

S. PetersA. AddeoM. DasH. HorinouchiT. SequeiraC. LovlyD. PlanchardS. PatelA. CortelliniN. FrostG. MountziosA. Dingemans
Jul 05 2026
ESMO 2026 SYMPOSIUM
SCLC

SCLC Symposium at ESMO 2026: From IO-Standards to the TCE Era

A symposium at ESMO Congress 2026 on small-cell lung cancer, from immunotherapy standards to the emerging era of DLL3 T-cell engagers. Recording to follow.

M. ReckS. PetersG. MountziosN. Reguart
Sep 26 2025
ILCS 2025
SCLC

Reshaping Approaches in SCLC with the Latest Advances in LS- and ES-Disease

} 34 min

R. Manochakian
Sep 26 2025
ILCS 2025
Advanced NSCLC

Latest Options for Non-Oncogene Addicted Advanced NSCLC in Frontline and Beyond

} 32 min

A. Curioni-Fontecedro
Sep 26 2025
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Latest Advances in Frontline EGFR+ NSCLC

} 14 min

A. Curioni-Fontecedro
Sep 26 2025
INDUSTRY SYMPOSIUM
Advanced NSCLCTargeted Therapies

Unlocking New Potentials in EGFR-Mutant NSCLC

} 30 min

A. Passaro
Sep 26 2025
ILCS 2025
ADCs

The ADC Revolution in Lung Cancer: New Targets, New Opportunities

} 27 min

N. Reguart
Sep 26 2025
ILCS 2025
Targeted Therapies

DEBATE: Which Is the Better Choice in EGFR+ Advanced NSCLC?

} 31 min

T. Newsom-DavisX. Le
Sep 26 2025
ILCS 2025
Targeted Therapies

Actionable Genomic Alterations – Including HER2 and MET

} 26 min

S. Saw
Sep 26 2025
ILCS 2025
Targeted Therapies

Targeting EGFR and ALK in NSCLC

} 26 min

T. John
Articles
Oct 23 2026
RESEARCH
SCLCImmunotherapies

KEYVIBE-008 tested vibostolimab coformulated with pembrolizumab plus chemotherapy in first-line ES-SCLC

J. SandsM. Reck
Oct 21 2026
SPONSORED
Advanced NSCLCImmunotherapies

The “tail of the curve” is real: long-term survival in PD-L1–negative metastatic NSCLC

A. Curioni-Fontecedro
Oct 21 2026
RESEARCH
Advanced NSCLCBiomarkersResectable NSCLC

ctDNA on immunotherapy is prognostic across NSCLC stages, but ctDNA-guided treatment remains investigational

U. Malapelle
Oct 19 2026
RESEARCH
Advanced NSCLCImmunotherapies

Nivolumab plus ipilimumab in 545 Japanese patients with metastatic NSCLC: the LIGHT-NING 2.5-year update

H. Horinouchi
Oct 15 2026
NEWS
Resectable NSCLC

A papal diagnosis turns the world’s attention to its most diagnosed cancer

Oct 14 2026
RESEARCH
Resectable NSCLC

More lymph nodes examined at segmentectomy tracked with longer survival in early-stage NSCLC

J. Perentes
Oct 06 2026
RESEARCH
Advanced NSCLCImmunotherapies

Two-thirds of patients with PD-L1-high NSCLC received first-line immunotherapy alone in a real-world survey

D. Rodríguez-Abreu
Oct 05 2026
RESEARCH
SCLCImmunotherapies

Second-line therapy in ES-SCLC gave a median OS of 7.1 months in the Austrian LALUCA registry

M. Hochmair
Oct 04 2026
RESEARCH
SCLCImmunotherapies

Longer OS in Asian than non-Asian patients given atezolizumab plus chemotherapy for extensive-stage SCLC

S. LiuM. ReckC. Rudin
Oct 03 2026
RESEARCH
Advanced NSCLCResectable NSCLCTargeted Therapies

AI-extracted records describe stage I–III NSCLC care at four Spanish hospitals before immunotherapy

A. Calles
Oct 02 2026
RESEARCH
Advanced NSCLCBiomarkersImmunotherapies

High tumour mutational burden was associated with more frequent and earlier immune-related adverse events in advanced NSCLC

B. Ricciuti
Sep 30 2026
RESEARCH
Resectable NSCLC

Spread through air spaces predicted relapse after both lobectomy and segmentectomy in JCOG0802 stage IA NSCLC

S. BerezowskaL. BubendorfP. Hofman
Martin Reck
Sep 28 2026
RESEARCH
Resectable NSCLCImmunotherapies

AEGEAN’s second interim analysis kept the EFS benefit of perioperative durvalumab, on an OS reading that crosses 1

M. ReckM. Hochmair
Sep 26 2026
RESEARCH
Advanced NSCLCImmunotherapies

Incidental thymic radiation dose was independently associated with metastasis and death in 1107 patients with NSCLC

B. Ricciuti
Sep 25 2026
RESEARCH
Resectable NSCLCTargeted Therapies

Multi-omic profiling separated recurrence risk within pathological stage in resected EGFR-mutant lung adenocarcinoma

S. Saw
Sep 19 2026
RESEARCH
Resectable NSCLC

Spread through air spaces carried an HR of 2.32 for DFS in stage 1 lung adenocarcinoma

S. Saw
Sep 17 2026
CONGRESS
Resectable NSCLCTargeted Therapies

Adjuvant osimertinib reduced the risk of death by 47% at eight years in ADAURA

Sep 15 2026
CONGRESS
Advanced NSCLCImmunotherapies

HARMONi-2: ivonescimab extends overall survival over pembrolizumab in China

Sep 15 2026
CONGRESS
Advanced NSCLCBiomarkersResectable NSCLC

WCLC 2026, day 4: tumour budding, BRAF class II and III, brain radiotherapy timing, and mobile CT screening

Sep 14 2026
CONGRESS
Resectable NSCLCTargeted Therapies

ADAURA at eight years: adjuvant osimertinib keeps a 15-point overall survival lead