SELECT FROM MENU

Therapy Areas
Drug Classes

       Therapy Areas

All Sessions

All Sessions

Resectable NSCLC

Resectable NSCLC

Advanced NSCLC

Advanced NSCLC

SCLC

SCLC

Biomarkers

Biomarkers

       Drug Classes

Targeted Therapies

Targeted Therapies

Immunotherapies

Immunotherapies

ADCs

ADCs

Advanced NSCLCSeptember 13, 2026

EVOKE-03: sacituzumab govitecan plus pembrolizumab misses both primary endpoints

Adding the Trop-2 antibody-drug conjugate sacituzumab govitecan to first-line pembrolizumab did not significantly prolong progression-free survival or overall survival in patients with metastatic non-small cell lung cancer and a PD-L1 tumour proportion score of 50% or more, according to the primary analysis of the phase 3 EVOKE-03/KEYNOTE-D46 trial. Presented by Dr. Giannis Mountzios of the Henry Dunant Hospital Center, Athens, Greece, at the Presidential Symposium of the IASLC 2026 World Conference on Lung Cancer (WCLC) in Seoul on 13 September, the trial recorded a numerically longer median PFS and a higher response rate with the combination, neither of which translated into a statistically significant benefit. Dr. Mountzios is a member of the Lung Summit faculty.
Share

In brief

  • EVOKE-03/KEYNOTE-D46 did not meet its primary endpoint: median PFS was 11.8 months with sacituzumab govitecan plus pembrolizumab versus 7.7 months with pembrolizumab alone (HR 0.81, 95% CI 0.66–1.00), but the one-sided P value of 0.0252 did not cross the boundary of 0.007.
  • At the interim analysis, overall survival was not improved: median 21.5 versus 22.8 months (HR 1.07, 95% CI 0.85–1.35; P = 0.7155).
  • Confirmed response rate was 55.6% versus 43.7% and disease control 83.3% versus 73.1%; median duration of response was 21.4 versus 21.3 months.
  • Grade 3 or higher treatment-emergent adverse events occurred in 73.6% of the combination arm and 45.0% of the pembrolizumab arm; no new toxicities were reported.

Study at a glance

  • Trial: EVOKE-03/KEYNOTE-D46 (NCT05609968)
  • Design: open-label, multicentre, randomised phase 3; international (stratified by region: East Asia; Western Europe/North America/Australia; rest of world); funded by Gilead Sciences and Merck Sharp & Dohme
  • Population: 620 patients with previously untreated stage IV NSCLC, PD-L1 TPS ≥50%, ECOG PS 0–1, no EGFR, ALK or ROS1 alteration
  • Arms: sacituzumab govitecan 10 mg/kg on days 1 and 8 plus pembrolizumab 200 mg on day 1 of each 21-day cycle (n = 311) versus pembrolizumab 200 mg alone (n = 309), up to 35 cycles of pembrolizumab
  • Dual primary endpoints: PFS by blinded independent central review (not met) and overall survival (not met at the interim analysis)
  • Data cut-off 3 April 2026; median follow-up 14.7 months

Two primary endpoints, each with its own significance boundary

The rationale for the trial comes from the limits of first-line immunotherapy. According to the presentation, more than half of patients with metastatic NSCLC do not respond to first-line pembrolizumab monotherapy. Sacituzumab govitecan is a Trop-2-directed antibody-drug conjugate carrying the topoisomerase I inhibitor payload SN-38. The phase 2 EVOKE-02 study had tested it with pembrolizumab in the first-line setting and, as described by the investigators, showed encouraging preliminary activity across histologies and in the PD-L1 TPS ≥50% subgroup.

EVOKE-03/KEYNOTE-D46 randomised 620 patients 1:1 to the combination or to pembrolizumab alone, stratified by ECOG performance status, predominant histology and geographic region. The population was 70% to 73% male, with a median age of 67 to 68 years; about 31% had squamous histology and about 17% had never smoked. Brain metastases were present in 8.7% and 9.7% of patients in the two arms, and liver metastases in about 16% of each. One patient in the pembrolizumab arm had a PD-L1 TPS below 50%.

The trial used a dual primary endpoint design with alpha split between the two endpoints: 0.007 for PFS and 0.018 for OS, with objective response rate as a secondary endpoint alongside duration of response, patient-reported outcomes and safety. A one-sided P value below 0.05 for PFS was therefore not sufficient on its own.

Median PFS 4.1 months longer, but the boundary was not crossed

At the primary PFS analysis, with 367 events (59% maturity) and a median follow-up of 14.8 months in the combination arm and 14.4 months in the control arm, median PFS by blinded independent central review was 11.8 months (95% CI 8.9–14.5) with sacituzumab govitecan plus pembrolizumab and 7.7 months (95% CI 5.6–9.7) with pembrolizumab alone. The stratified hazard ratio was 0.81 (95% CI 0.66–1.00) and the one-sided P value 0.0252, above the prespecified boundary of 0.007. The 12-month PFS rate was 48.3% versus 36.9%, and the 18-month rate 36.0% versus 29.9%.
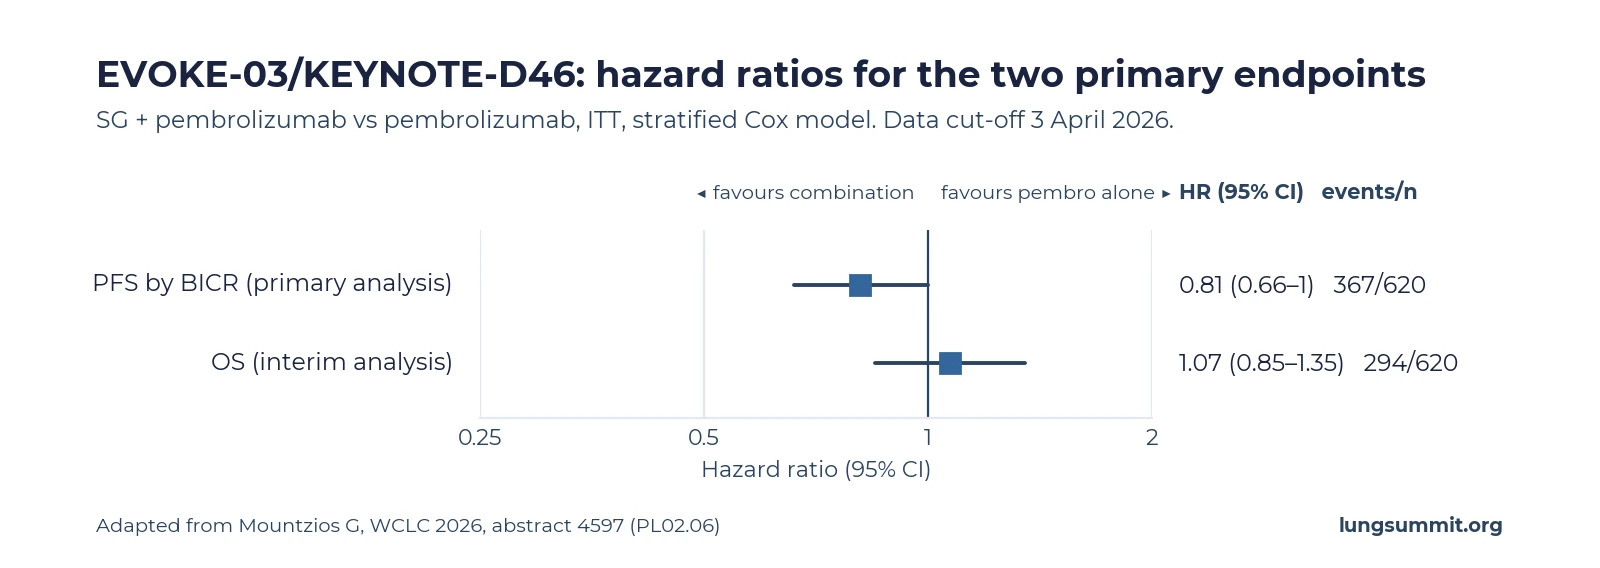
Forest plot of EVOKE-03 hazard ratios: progression-free survival 0.81 with 95 percent confidence interval 0.66 to 1.00, and overall survival 1.07 with 95 percent confidence interval 0.85 to 1.35. Both intervals cross 1.
Figure 1. Hazard ratios for the dual primary endpoints of EVOKE-03/KEYNOTE-D46 in the intention-to-treat population: 0.81 (95% CI 0.66–1.00; one-sided P = 0.0252 against a boundary of 0.007; 367 events) for progression-free survival by blinded independent central review, and 1.07 (95% CI 0.85–1.35; P = 0.7155 against a boundary of 0.008; 294 events) for overall survival at the interim analysis. Neither reached statistical significance. Adapted from Mountzios G, WCLC 2026, abstract 4597 (PL02.06).

The interim overall survival analysis, with 294 events (47% maturity, 80% information fraction), showed no advantage for the combination. Median OS was 21.5 months (95% CI 18.5–26.7) with sacituzumab govitecan plus pembrolizumab and 22.8 months (95% CI 18.7–29.0) with pembrolizumab alone, a hazard ratio of 1.07 (95% CI 0.85–1.35; P = 0.7155 against a boundary of 0.008). PFS subgroup analyses were presented as unstratified hazard ratios; subgroups representing fewer than 10% of the intention-to-treat population were not analysed, and the values are not reproduced here.

In the IASLC news release, Dr. Mountzios summarised the result.

“While the combination of sacituzumab govitecan and pembrolizumab produced a numerically longer progression-free survival and a higher response rate, EVOKE-03/KEYNOTE-D46 did not meet statistical significance for its primary PFS endpoint, and overall survival was not significantly improved at this interim analysis,”Dr. Giannis Mountzios, Henry Dunant Hospital Center, Athens, Greece

A post-hoc look at East Asian and Chinese patients

The investigators also presented a post-hoc analysis of overall survival by region, which they stated was neither pre-specified nor pre-stratified. In the East Asian cohort (114 versus 116 patients, median follow-up 18.1 months), median OS was not reached with the combination (95% CI 24.3 months to not evaluable) versus 27.9 months (95% CI 16.7 to not evaluable) with pembrolizumab alone, hazard ratio 0.73 (95% CI 0.48–1.10). In the Chinese subgroup (52 versus 55 patients, median follow-up 22.4 months), median OS was again not reached versus 27.9 months, hazard ratio 0.65 (95% CI 0.36–1.16). Both confidence intervals include 1, the analyses were unstratified, and the presentation drew no conclusion from them beyond reporting the figures.

Response rate 12 points higher, duration of response identical

The secondary endpoints separated more clearly than the primary ones. Confirmed objective response by blinded independent central review was 55.6% (95% CI 49.9–61.2) with sacituzumab govitecan plus pembrolizumab and 43.7% (95% CI 38.1–49.4) with pembrolizumab alone, a difference the investigators put at about 12 percentage points. Complete responses were recorded in 7.7% versus 3.9% of patients and partial responses in 47.9% versus 39.8%. Progressive disease as best response was less frequent with the combination, 7.1% versus 16.5%. Disease control was 83.3% (95% CI 78.7–87.3) versus 73.1% (95% CI 67.8–78.0).

Bar chart of EVOKE-03 secondary endpoints: confirmed objective response rate 55.6 percent with sacituzumab govitecan plus pembrolizumab versus 43.7 percent with pembrolizumab, and disease control rate 83.3 percent versus 73.1 percent.
Figure 2. Confirmed objective response rate (55.6% vs 43.7%) and disease control rate (83.3% vs 73.1%) by blinded independent central review with sacituzumab govitecan plus pembrolizumab versus pembrolizumab alone in the intention-to-treat population of EVOKE-03/KEYNOTE-D46. Both are secondary endpoints; median duration of response was 21.4 versus 21.3 months. Adapted from Mountzios G, WCLC 2026, abstract 4597 (PL02.06).

Responses, once achieved, lasted about as long in both arms: median duration of response was 21.4 months (95% CI 14.9 to not estimable) with the combination and 21.3 months (95% CI 15.7 to not estimable) with pembrolizumab alone. No post-baseline assessment was available for 8.4% and 8.1% of patients, respectively.

Grade 3 or higher events in 73.6% versus 45.0%

The safety population comprised 307 patients in the combination arm and 309 in the pembrolizumab arm. Median exposure to study drug was 8.5 months with the combination and 6.2 months with pembrolizumab alone. Treatment-emergent adverse events of any grade occurred in 98.4% versus 95.1% of patients, and grade 3 or higher events in 73.6% versus 45.0%. Serious treatment-emergent events were reported in 53.4% versus 39.5%, and events leading to discontinuation of any study drug in 30.9% versus 20.1%.

Adverse events leading to death occurred in 35 patients (11.4%) in the combination arm and 30 (9.7%) in the control arm. Nine deaths were considered treatment-related: five with the combination (immune-mediated lung disease, pneumonia in two patients, interstitial lung disease and pneumonitis), of which the investigators noted not all were attributed to sacituzumab govitecan, and four with pembrolizumab alone (pneumonitis, pulmonary embolism, myocarditis and immune-mediated lung disease, one each).

The events reported in more than 15% of patients in the combination arm were, in order of frequency, anaemia (44% of patients, grade 3 or higher in 8%), alopecia (41%), neutropenia (40%, grade 3 or higher in 24%), diarrhoea (32%), nausea (30%), fatigue (30%), leukopenia (29%, grade 3 or higher in 8%), decreased appetite (21%), rash (16%), raised ALT (15%) and pruritus (15%). In the pembrolizumab arm none of these exceeded 10%. The investigators characterised the profile as consistent with each agent used alone, with no new or additional toxicities from the combination.

The investigators concluded that the combination produced a numerically longer PFS that did not reach statistical significance, a higher response and disease control rate, a similar duration of response, and no significant difference in overall survival at the interim analysis. The OS analysis was conducted at an 80% information fraction; the presentation gave no date for the final analysis.

Sources

  1. Mountzios G, et al. Primary results from phase 3 EVOKE-03/KEYNOTE D46: sacituzumab govitecan + pembrolizumab in PD-L1 TPS ≥50% metastatic NSCLC. IASLC 2026 World Conference on Lung Cancer, Seoul, 12–15 September 2026; abstract 4597 (session PL02.06).
  2. IASLC news release, Seoul, 13 September 2026: “Sacituzumab Govitecan Plus Pembrolizumab Does Not Meet Primary Endpoints in First-Line PD-L1-High Metastatic NSCLC”.

ILCS 2026

The International Lung Cancer Summit (ILCS 2026) takes place on Friday 13 November 2026 in Lausanne and live online. Faculty will discuss the WCLC 2026 data in the context of daily practice. Register for ILCS 2026 →

Written by the Lung Summit editorial team.

This article was produced independently by the Lung Summit editorial team, without industry funding or input.

i 3 On This Page

Share

       Continue With

Related Topics

Videos
Jacob Sands, Solange Peters and Martin Reck
Dec102026
VIRTUAL ROUNDTABLE
Advanced NSCLCSCLCADCs

2026 Year in Review

Learn more about the event

S. PetersJ. SandsM. Reck
Nov 13 2026
ILCS 2026
Advanced NSCLCResectable NSCLCSCLC

Panel: open questions & patient cases

Nov 13 2026
ILCS 2026
Advanced NSCLC

New compounds and combinations for non-oncogene-addicted advanced NSCLC

A. Cortellini
Nov 13 2026
ILCS 2026
Resectable NSCLCImmunotherapies

Latest options in early-stage NSCLC: novel IO approaches for improved outcomes

S. Patel
Nov 13 2026
INDUSTRY SYMPOSIUM
Advanced NSCLCResectable NSCLCTargeted Therapies

One Backbone, Many Opportunities: Osimertinib Across the EGFRm NSCLC Journey

M. Hochmair
Nov 13 2026
INDUSTRY SYMPOSIUM
Advanced NSCLCTargeted Therapies

First-Line NSCLC in Transition: Opportunities and Challenges for KRAS G12C

A. Curioni-Fontecedro
Nov 13 2026
ILCS 2026
Advanced NSCLCADCs

The ADC wave: integrating new agents in NSCLC

D. Planchard
Nov 13 2026
ILCS 2026
Advanced NSCLCTargeted Therapies

Targeting (K)RAS with new compounds

C. Lovly
Nov 13 2026
ILCS 2026
Advanced NSCLCTargeted Therapies

Other actionable genomic alterations, incl. HER2 and ROS1

T. Sequeira
Nov 13 2026
ILCS 2026
Advanced NSCLCTargeted Therapies

New standards in EGFR- and ALK-positive NSCLC

H. Horinouchi
Prof. Martin Reck
Nov 04 2026
SPONSORED EXPERT TALK
Resectable NSCLCImmunotherapies

MDT-BRIDGE in Resectable and Borderline Resectable NSCLC

Prof. Martin Reck presents and discusses the phase 2 MDT-BRIDGE trial in resectable and borderline resectable non-small cell lung cancer in this on-demand expert talk.

M. Reck
Dr. Jacob Sands
Nov 04 2026
SPONSORED INTERVIEW
SCLCImmunotherapies

New Therapy Options in SCLC and AE Management

Dr. Jacob Sands discusses new treatment options in small cell lung cancer and the management of their adverse events in this on-demand expert interview.

J. Sands
Oct252026
ESMO 2026 SYMPOSIUM
SCLCImmunotherapies

SCLC Symposium at ESMO 2026: From IO-Standards to the TCE Era

A symposium at ESMO Congress 2026 on small-cell lung cancer, from immunotherapy standards to the emerging era of DLL3 T-cell engagers. Recording to follow.

M. ReckS. PetersG. MountziosN. Reguart
Oliver Gautschi on EGFR+ NSCLC
Jul 20 2026
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Advances in EGFR+ NSCLC: An Interview with Prof. Oliver Gautschi

Prof. Oliver Gautschi discusses recent advances in the treatment of EGFR-mutant non-small cell lung cancer in this on-demand expert interview.

O. Gautschi
Prof. Alessandra Curioni-Fontecedro discussing approaches in metastatic PD-L1 negative NSCLC
May 04 2026
SPONSORED INTERVIEW
Advanced NSCLCImmunotherapies

Approaches in Metastatic PD-L1 Negative NSCLC: An Interview with Prof. Alessandra Curioni-Fontecedro

Prof. Alessandra Curioni-Fontecedro discusses treatment approaches in metastatic PD-L1 negative non-small cell lung cancer in this on-demand expert interview.

A. Curioni-Fontecedro
Lung Cancer Review by Solange Peters, Martin Reck, Charles Rudin
Dec 18 2025
VIRTUAL ROUNDTABLE
Advanced NSCLCSCLCADCs

2025 Approvals & Highlights

} 1 h 49 min

S. PetersC. RudinM. Reck
Sep 26 2025
ILCS 2025
Advanced NSCLC

Latest Options for Non-Oncogene Addicted Advanced NSCLC in Frontline and Beyond

} 32 min

A. Curioni-Fontecedro
Sep 26 2025
ILCS 2025
Immunotherapies

The Role of IO Added to Chemoradiation in Unresectable Stage III NSCLC

} 28 min

A. Filippi
Sep 26 2025
ILCS 2025
Immunotherapies

Tailoring IO in Res. NSCLC: Personalized Approaches for Improved Outcomes

} 36 min

P. Forde
Sep 26 2025
SPONSORED INTERVIEW
Advanced NSCLCTargeted Therapies

Latest Advances in Frontline EGFR+ NSCLC

} 14 min

A. Curioni-Fontecedro
Articles
Nov 16 2026
RESEARCH
Advanced NSCLCResectable NSCLC

South Asian experts agree consensus recommendations for NSCLC, with low-cost options built in

V. Noronha
Nov 16 2026
RESEARCH
Immunotherapies

Lenvatinib plus pembrolizumab gave a median PFS of 22.1 months in pretreated thymic carcinoma and B3 thymoma

J. RemonN. GirardN. Reguart
Nikolaj Frost
Nov 15 2026
RESEARCH
Advanced NSCLCResectable NSCLC

A 454-patient single-cell atlas links NSCLC tumour cell states to metastasis and survival

N. Frost
Charles Rudin
Nov 14 2026
RESEARCH
Advanced NSCLCSCLCTargeted Therapies

SCLC transformation in 5 of 11 patients given first-line osimertinib with platinum and etoposide

C. Rudin
Nov 14 2026
RESEARCH
Advanced NSCLCBiomarkersADCs

Membrane share of TROP2 identified longer PFS on Dato-DXd in nonsquamous NSCLC

J. SandsM. PérolN. Girard
Nov 04 2026
RESEARCH
Advanced NSCLCImmunotherapies

Local ablative therapy alone after durvalumab was followed by an mOS of 18.7 months in oligoprogressive NSCLC

A. FilippiL. Hendriks
Nov 01 2026
RESEARCH
Advanced NSCLCBiomarkersTargeted Therapies

Secondary ALK resistance mutations found in 8% of ALK-positive NSCLC samples on genomic profiling

P. Hofman
Nikolaj Frost
Oct 31 2026
RESEARCH
Resectable NSCLCImmunotherapies

KEYNOTE-867 tested pembrolizumab with SBRT in unresected stage I or II NSCLC

N. Frost
Oct 31 2026
RESEARCH
Advanced NSCLCTargeted Therapies

VTE reporting in fusion-positive NSCLC trials is fragmented across publications and registries

A. Cortellini
Charles Rudin
Oct 30 2026
RESEARCH
SCLCImmunotherapies

Tarlatamab gave an mOS of 13.6 months against 8.4 with chemotherapy in SCLC at extended DeLLphi-304 follow-up

C. RudinG. Mountzios
Martin Reck
Oct 30 2026
RESEARCH
Advanced NSCLCResectable NSCLCImmunotherapies

Neoadjuvant durvalumab plus chemotherapy led to resection in 74.6% of patients in the MDT-BRIDGE trial

M. ReckN. GirardA. Filippi
Oct 29 2026
RESEARCH
BiomarkersResectable NSCLCImmunotherapies

Early ctDNA clearance was associated with longer event-free survival in resectable NSCLC in NeoCOAST-2

T. CasconeP. Forde
Oct 29 2026
RESEARCH
Advanced NSCLCImmunotherapies

Adding chemotherapy to pembrolizumab lengthened PFS in PD-L1-high advanced NSCLC in PERSEE

M. Pérol
Oct 27 2026
RESEARCH
SCLCImmunotherapies

Tarlatamab added to durvalumab maintenance extended OS in extensive-stage SCLC

J. SandsM. PérolA. Dingemans
Oct 26 2026
INDUSTRY NEWS
Advanced NSCLCResectable NSCLCTargeted Therapies

Divarasib extended OS over sotorasib or adagrasib in previously treated KRAS G12C-mutated NSCLC

Oct 23 2026
RESEARCH
SCLCImmunotherapies

KEYVIBE-008 tested vibostolimab coformulated with pembrolizumab plus chemotherapy in first-line ES-SCLC

J. SandsM. Reck
Oct 22 2026
RESEARCH
Advanced NSCLC

TP53 Y220C occurs in 0.7% of NSCLC and more often in EGFR-mutant tumours, in an ETOP study of 28,244 patients

R. StahelL. BubendorfL. HendriksS. PetersS. Finn
Oct 21 2026
SPONSORED
Advanced NSCLCImmunotherapies

The “tail of the curve” is real: long-term survival in PD-L1–negative metastatic NSCLC

A. Curioni-Fontecedro
Oct 21 2026
RESEARCH
Advanced NSCLCBiomarkersResectable NSCLC

ctDNA on immunotherapy is prognostic across NSCLC stages, but ctDNA-guided treatment remains investigational

U. Malapelle
Oct 19 2026
RESEARCH
Advanced NSCLCImmunotherapies

Nivolumab plus ipilimumab in 545 Japanese patients with metastatic NSCLC: the LIGHT-NING 2.5-year update

H. Horinouchi